

The Engine Room in a Glass
Every time we flex a muscle, take a breath, or blink an eye, our body spends a tiny packet of…
Medical Disclaimer: The information provided in this article is for educational and informational purposes only and is not intended as personal medical advice, diagnosis, or treatment. Always consult with a qualified healthcare professional regarding any medical condition or dietary supplementation.
When it comes to diagnostic medicine, a test is generally most valuable when its result dictates a clear, actionable change in medical care. If a positive test and a negative test lead to the exact same clinical strategy, routine screening offers minimal practical benefit.
In the realm of nutritional health, Vitamin B12 testing frequently creates this exact dilemma. Because Vitamin B12 plays a vital role in neurological function, red blood cell synthesis, and DNA production, maintaining adequate levels is essential. However, the decision to run a blood test should be strategic. For many healthy individuals, standard diagnostic pathways can be surprisingly misleading.
This comprehensive guide examines who genuinely requires testing, the physiological limitations of standard B12 assays, the superior accuracy of the Active B12 (holotranscobalamin) test, and the unique factors driving high rates of Vitamin B12 deficiency across India.
In clinical practice, diagnostic tests should serve as decision-making tools. For a low-risk, asymptomatic healthy adult, broad-scale routine B12 screening often falls short of this threshold.
Consider the practical outcomes: if an individual tests low for Vitamin B12, the standard medical recommendation is to begin a safe, reliable B12 supplement. Conversely, if a person presenting with subtle symptoms tests within the “normal” range on a standard assay, the recommendation given the known rate of false negatives might still be to supplement or perform follow-up testing.
When both low and normal test results ultimately point toward the same low-risk intervention (such as taking a high-quality oral B12 supplement or adjusting diet), routine testing for healthy individuals primarily adds financial cost and unnecessary health anxiety without significantly altering the clinical management plan.
To illustrate this logic, consider an asymptomatic individual eating a plant-based diet who chooses to take a daily maintenance dose of B12. Performing an expensive blood test simply to confirm that a low-risk dietary supplement is necessary rarely alters their daily routine or treatment trajectory.
While blanket screening for asymptomatic, low-risk populations is debatable, clinical testing becomes critical for specific groups. Medical evaluation is strongly indicated for:
The traditional total serum Vitamin B12 test measures the entire concentration of B12 circulating in the bloodstream. While it remains the standard initial screening tool worldwide, it carries a significant limitation: a “normal” total B12 result does not necessarily mean your tissues are receiving sufficient B12.
According to clinical research, a normal total serum cobalamin concentration does not rule out a functional cobalamin deficiency at the cellular level, and no single diagnostic metric alone offers a complete picture. Total B12 tests measure both biologically active B12 and inactive B12 bound to transport proteins that cannot deliver the nutrient to cells. As a result, many patients receive false reassurance from a normal test result while actively experiencing cellular deprivation.
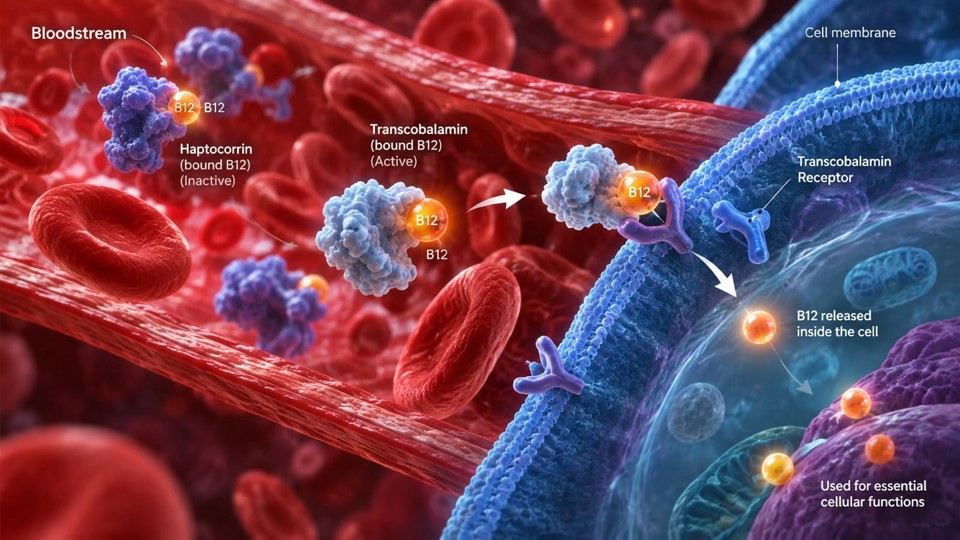
Vitamin B12 in the blood is primarily bound to two carrier proteins: haptocorrin and transcobalamin. Haptocorrin binds roughly 70% to 80% of circulating B12, rendering it inert and inaccessible to body tissues. Transcobalamin carries the remaining 20% to 30%, which is the only form cells can absorb and use.
Standard tests measure both pools combined. If a person has high levels of inactive B12 bound to haptocorrin, their total B12 score may look completely healthy, even if their cell-usable B12 is dangerously low.
To circumvent this limitation, clinicians traditionally order a Methylmalonic Acid (MMA) test. MMA levels rise when cellular B12 is deficient, acting as a functional biomarker. However, MMA testing can be expensive and is not universally available in all basic laboratory panels.
To address the diagnostic flaws of total serum assays, modern pathology has turned to the Active B12 test, technically known as the holotranscobalamin (holoTC) test.
Holotranscobalamin represents only the fraction of B12 that is bound to transcobalamin. Because this is the exact form of B12 that can cross cell membranes and support biological functions, measuring holoTC evaluates the B12 that is actually available for cellular uptake. By excluding the inactive haptocorrin-bound portion, the Active B12 test provides an accurate reflection of metabolic B12 status.
Understanding the distinction comes down to what is being measured:
Clinical studies consistently demonstrate the clinical superiority of Active B12 over traditional testing:
Despite these clear diagnostic advantages, it is important to note that global medical adoption remains ongoing. Certain healthcare organizations and payer policies, such as specific medical coverage guidelines in the United States, still classify holotranscobalamin testing as an investigational or secondary tool for routine screening. Thus, while Active B12 is increasingly recognized for its heightened sensitivity, it is best understood as a superior diagnostic alternative rather than a universally mandated replacement in every clinical setting.
Interpreting Active B12 results requires evaluating the specific reference ranges set by the analyzing laboratory. Because testing kits and assay equipment vary across diagnostic centers, precise numerical cutoffs must always be verified against the reporting lab’s reference guide.
In general clinical practice, reference ranges function according to a clear biological logic:
Note: Reference intervals vary by manufacturer and laboratory. While some diagnostic platforms set cutoffs around 20 to 30 pmol/L for deficiency, others utilize thresholds above 70 pmol/L for normal status. Always reference the specific cutoff printed on your lab report.
When a deficiency is identified, restoring optimal B12 levels is straightforward, safe, and highly effective. Treatment typically relies on either high-dose oral supplementation or intramuscular injections.
Both routes aim to replenish depleted tissue stores:
Historically, medical practice favored intramuscular injections under the assumption that oral B12 could not be absorbed sufficiently without robust intrinsic factor production in the stomach. Modern clinical trials have updated this perspective:
In clinical practice, physicians often utilize a short phase of high-dose supplementation (e.g., 2,000 mcg daily for two weeks) followed by a maintenance dose, though specific protocols should always be determined by a patient’s treating physician.
Vitamin B12 deficiency represents a major public health challenge in India. Epidemiological studies highlight an extraordinarily high prevalence of sub-optimal B12 status across nearly all demographics.
While plant-based diets are a key contributor, dietary choices alone do not explain the scale of the issue. Research across India shows wide variations in deficiency rates, ranging generally from 16% to 77% depending on the specific region, age group, and lab cutoff used. Among pregnant women, deficiency estimates range between 43% and 74% in various regional studies.
Crucially, meat consumption does not guarantee protection against B12 deficiency. A study conducted by the National Institute of Nutrition (NIN) in Telangana – a state with high rates of non-vegetarian dietary habits—found that 44% of pregnant women surveyed were still B12 deficient.
Key contributing factors beyond diet include:
B12 deficiency often develops slowly over months or years. Common early indicators include:
If these symptoms persist, individuals should consult a healthcare professional for a thorough diagnostic review.
Yes, in terms of diagnostic sensitivity. The Active B12 test measures only holotranscobalamin—the cell-usable form of the vitamin. Traditional B12 tests measure both active and inactive B12, which can result in false-normal scores even when cellular deficiency is present.
For most healthy, non-pregnant adults, taking a standard oral B12 supplement is considered safe because Vitamin B12 is water-soluble, meaning excess amounts are excreted in urine. However, if you are experiencing active neurological or severe symptoms, you should consult a doctor before starting treatment.
Not necessarily. Clinical evidence shows that high-dose oral B12 (e.g., 1,000 to 2,000 mcg daily) is as effective as intramuscular injections for restoring normal B12 blood levels over time, provided the dosage is sufficient. Injections are typically reserved for severe deficiencies or critical absorption disorders.
Deficiency rates in India are among the highest in the world, with studies estimating that between 16% and 77% of the population is affected depending on the demographic and diagnostic criteria used. High rates are observed among both vegetarians and non-vegetarians.

Every time we flex a muscle, take a breath, or blink an eye, our body spends a tiny packet of…

Managing chronic kidney disease through nutrition relies on balancing essential nutrients while minimising the workload on failing kidneys. Damaged kidneys…

Passing pink or reddish urine after eating beetroot is a harmless condition known as beeturia. While seeing a unexpected splash…
